


Quick Answer
A medication-readiness review, the pre-surgical screen that maps each drug to its specific effect on bone healing and clotting, predicts implant success more reliably than a patient's age. Blood thinners require bridging protocols. Bone medications require a MRONJ risk assessment. GLP-1 drugs and immunosuppressants each add a distinct evaluation step. The medication list a patient brings to the consultation shapes the entire implant plan before the first scan.
The question patients ask most often in an implant consultation is about age. "Am I too old?" It is a fair question, and the answer is almost always more encouraging than they expect. But the more telling question is a different one: "What medications are you currently taking?"
That second question predicts implant outcomes more reliably than a birth year. Blood thinners, bone medications, antidepressants, GLP-1 drugs, and immunosuppressants each interact with the biology of implant healing in a distinct way. A structured medication review identifies those interactions before the first implant is placed, not after it fails. Age is one factor. Medications are the factor.
According to evidence on pre-surgical screening protocols, the difference between a successful implant and a late failure often comes down to what was or was not disclosed before treatment began. Patients who arrive at a consultation with a complete medication list, including dosage and duration, navigate the planning conversation differently from those who assume that medications are irrelevant to dental surgery.
Four drug categories shape the risk profile most sharply: bisphosphonates (Fosamax, Prolia, Zometa), anticoagulants (warfarin, rivaroxaban, apixaban), systemic corticosteroids, and GLP-1 receptor agonists (Ozempic, Wegovy, semaglutide). Each belongs to a distinct risk tier. Each calls for a different protocol adjustment. Each is covered in detail in the sections below. A patient who understands which tier their medications fall into walks into that consultation prepared, and that preparation changes the quality of the plan they leave with.
Your age at the consultation matters far less than what is in your pharmacy drawer. When clinicians review a medication list before an implant appointment, the same drug classes keep appearing as the factors that change the surgical plan: bisphosphonates, blood thinners, SSRIs, corticosteroids, and GLP-1 drugs like Ozempic and Wegovy. Each one works on different biology, and each one reshapes the plan in a different way.
The picture that emerges from professional guidelines and published clinical research is consistent. A healthy 70-year-old with adequate bone density and a clean medication list is often a stronger implant candidate than a 35-year-old managing multiple systemic conditions across five prescriptions. Candidacy is not an age question. It is a biology question. Medications are where biology announces itself most clearly.
Not every drug on the list is a dealbreaker. Some require a protocol adjustment. Some need coordination with a prescribing physician. A few require specialist consultation before any surgical planning begins. Only a narrow category genuinely shifts a patient out of candidacy. Understanding which category applies to your situation is the purpose of the medication readiness review. It is where the real implant plan gets built.
Questions This Article Answers
- Can you get dental implants if you take Fosamax or other bisphosphonates for osteoporosis?
- Do antidepressants like SSRIs affect dental implant success rates?
- Do blood thinners disqualify you from getting dental implants?
Why Does Your Medication List Matter More Than Your Age for Dental Implants?
Your medication list, not your birthdate, is the factor most likely to change your implant plan. Most patients walk in worried about whether they are "too old," and walk out realizing the conversation is actually about five or six common prescriptions they have been taking for years.
An analysis of more than a dozen clinical sources, patient outcome reports, and professional guidelines shows one consistent finding: the drug classes that interfere with bone healing reshape a patient's plan more reliably than chronological age does. According to dentist and clinical writer Muhammad Ansar Khan in The Clinical Pen, "a healthy 70-year-old with adequate bone is a better candidate than an unhealthy 30-year-old with significant bone loss." Age, in other words, is context. Medications are the mechanism, as of .
The takeaway is clear. What your body is doing chemically matters more than how long you have been doing it. In practice, this means we look at your pharmacy printout with the same attention we give to your bone scan.
We call this the medication-readiness review, and it is the lens we use at Imagine Advanced Dental Arts before any implant plan is written. The review sorts every medication into one of four questions:
- Does this drug change how bone heals or fuses around an implant?
- Does this drug raise surgical bleeding risk?
- Does this drug affect anesthesia safety?
- Does this drug suppress the immune response that heals the surgical site?
A drug that answers "yes" to any of those questions gets a protocol adjustment, not an automatic denial. That distinction matters enormously. Patients on bisphosphonates, antidepressants, or blood thinners are routinely told they cannot have implants, when the evidence says their plan simply needs modification.
Contrary to what many patients hear at a first consultation, the vast majority of common medications do not eliminate candidacy. They change the timing, the monitoring schedule, or the coordination with a prescribing physician. The reality is that a blanket "no" based on a medication name alone is often a reflection of provider caution rather than clinical evidence.
The sections below walk through each major drug class in plain language: what it does to bone biology, how it changes the surgical plan, and what to expect when you bring your full medication list to a consultation at our Lawrenceville, NJ practice.
How Do Bone Medications Interfere With the Biology of Dental Implant Healing?
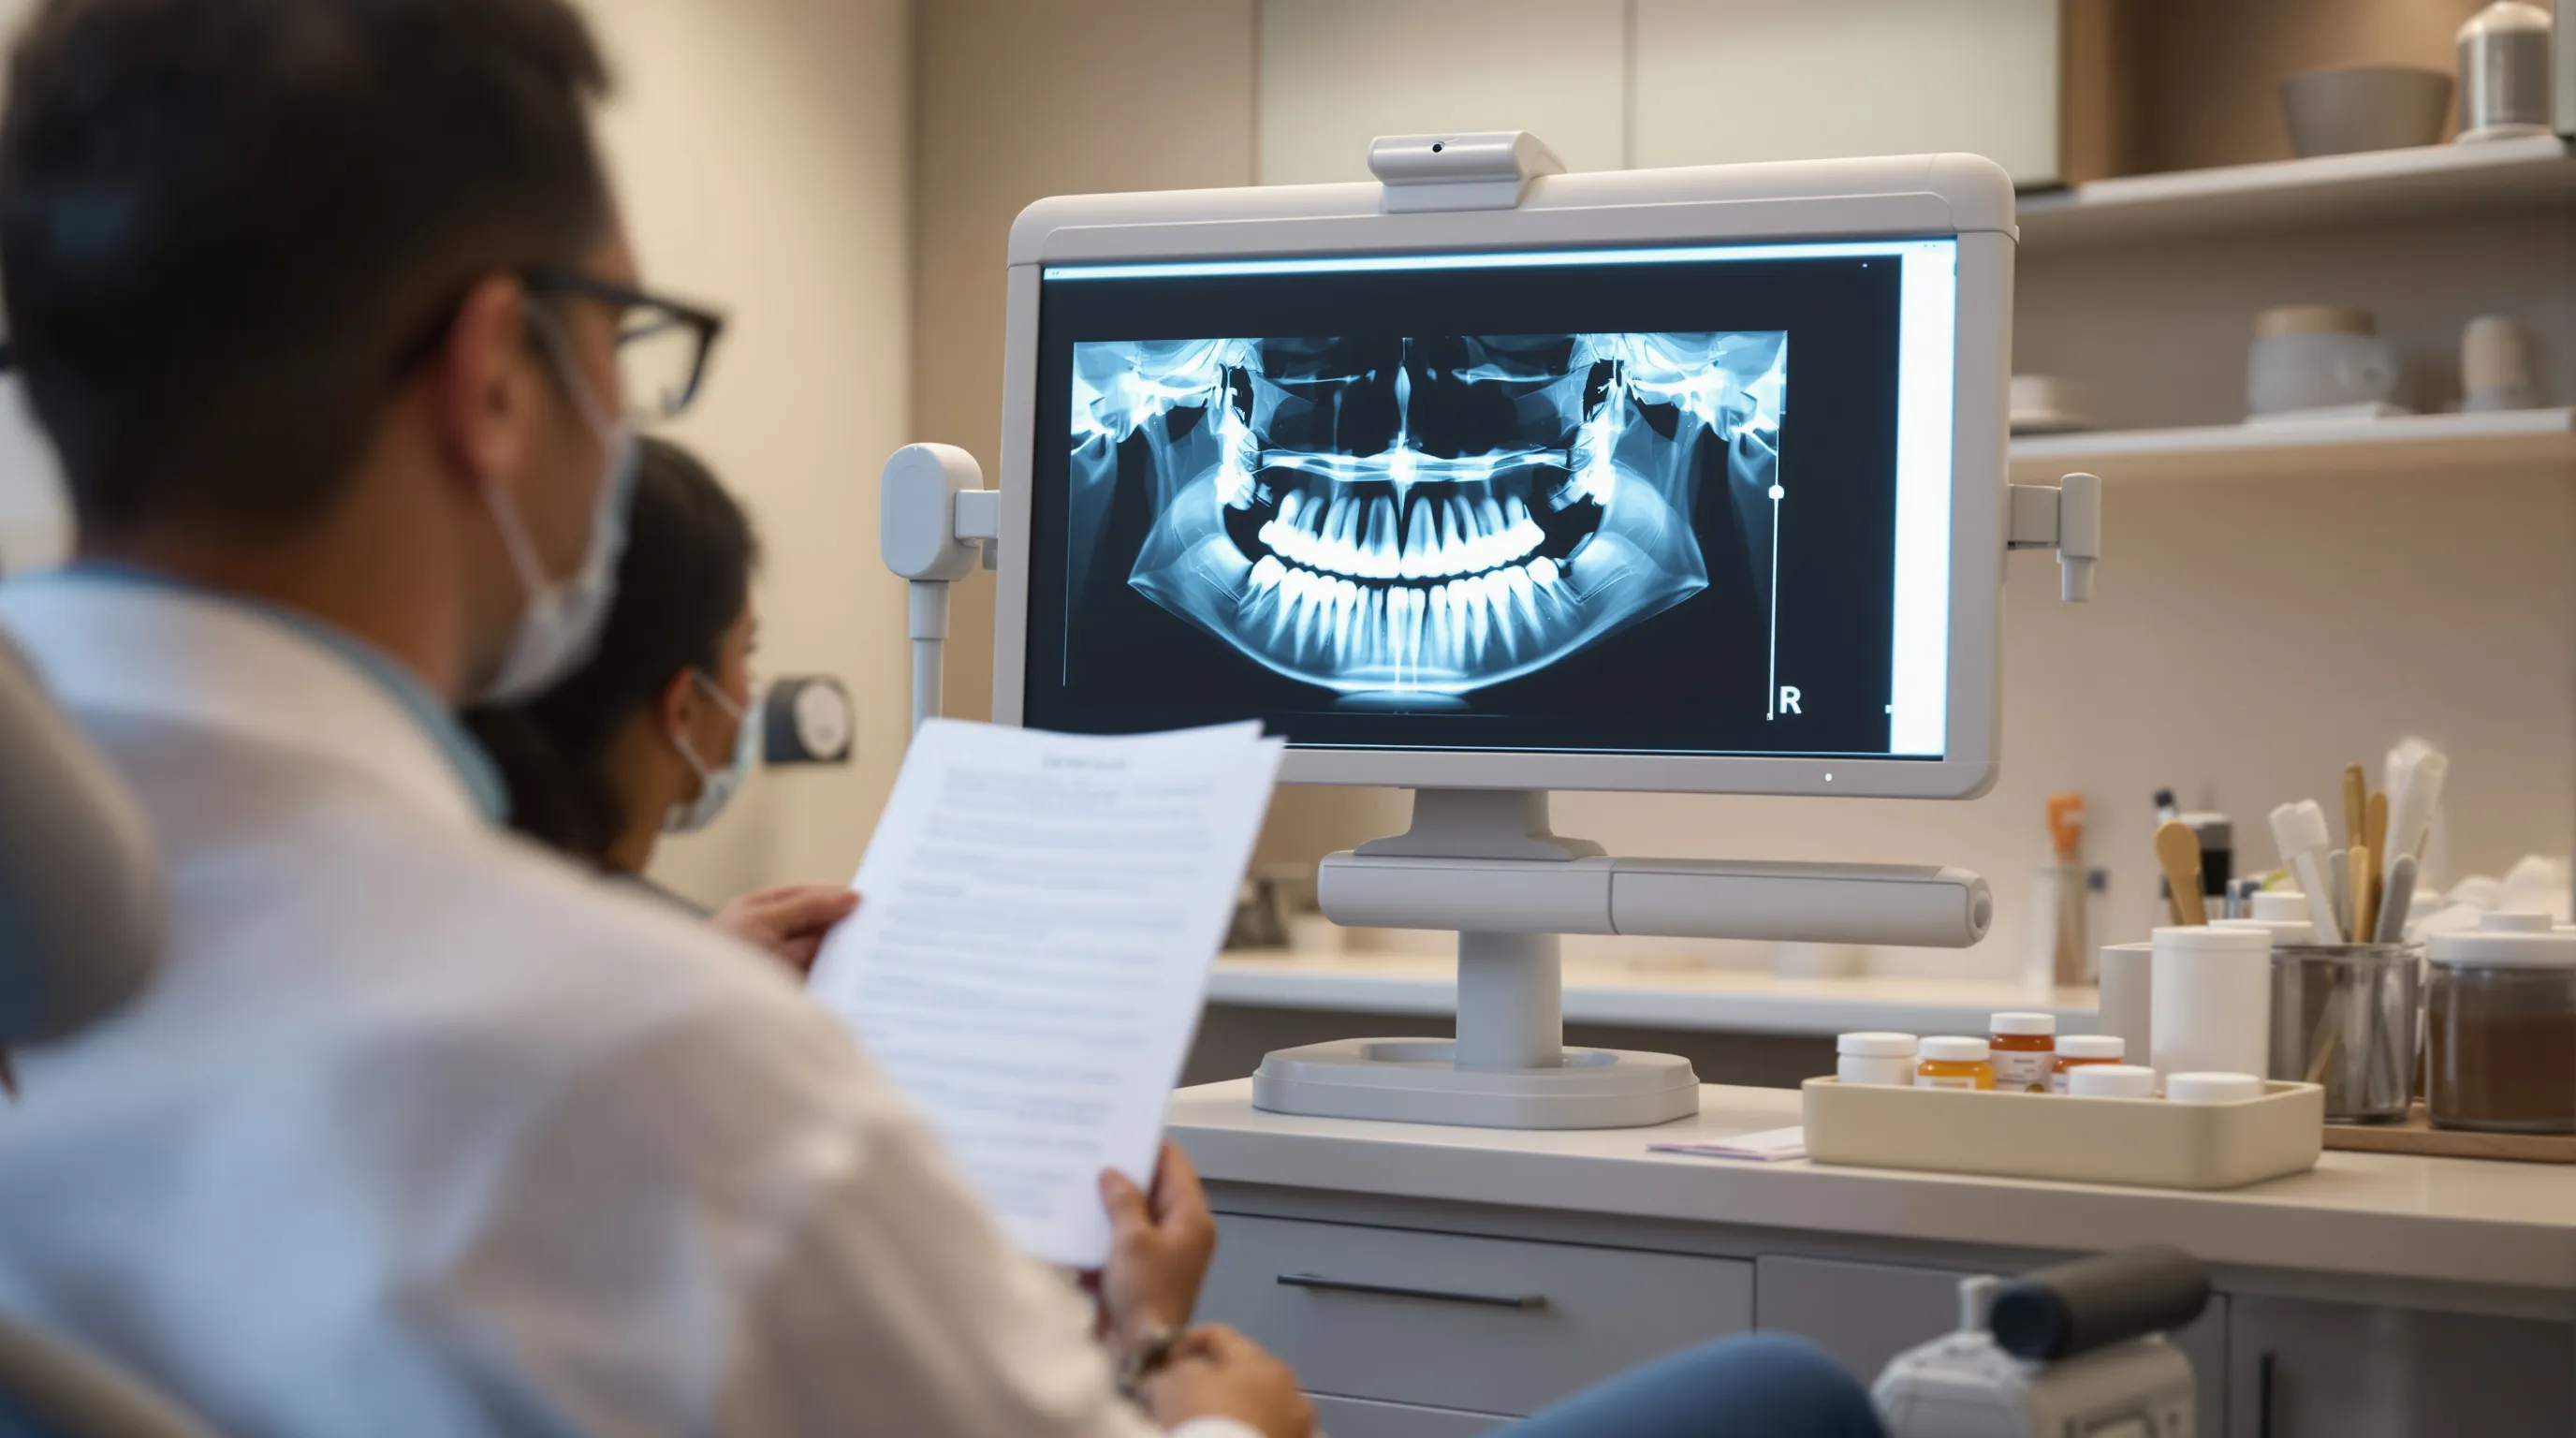
Bisphosphonates and long-term steroids both suppress bone cell activity, which is the very process an implant relies on to fuse permanently with your jaw.
To understand why, it helps to think about what osseointegration actually requires. After a titanium implant is placed, the surrounding bone must grow around it and bond to the surface over several months. That process demands active, healthy bone cells: osteoblasts building new bone structure, osteoclasts clearing away old bone tissue. Disrupt that cellular activity, and the implant has nowhere to anchor.
Bisphosphonates are designed to do exactly that, which is what makes them so valuable for treating osteoporosis. They slow bone cell activity so that existing bone is preserved. For day-to-day bone health, that is a benefit. After dental implant surgery, the same suppression can prevent the bone from integrating with the implant the way it needs to.
According to the American Association of Endodontists' guidelines on Medication-Related Osteonecrosis of the Jaw, bisphosphonates fall into two broad categories: oral forms (including alendronate, sold as Fosamax, and ibandronate, sold as Boniva) and intravenous forms used in cancer care (including zoledronate, sold as Zometa and Reclast). The AAE also flags RANK-L inhibitors like denosumab (Prolia) and antiangiogenic agents as carrying similar risks. The intravenous forms carry materially higher risk than the oral forms taken for osteoporosis.
The AAE guidelines note that osteonecrosis risk rises with long-term use (generally defined as more than three years) or when bisphosphonate use is combined with corticosteroids. In practice, this means a patient who has taken Fosamax for eight weeks faces a very different risk profile than someone on a decade-long regimen combined with prednisone. We see this distinction matter enormously in our Lawrenceville patients, and it is something we explore in detail before any treatment is planned.
Long-term steroid use adds a second layer of complexity. Prednisone and similar corticosteroids reduce bone density over time in ways that a bone scan may not fully capture. A patient on multi-year steroid therapy can have bone that looks adequate on imaging but responds differently to the stress of implant placement and loading.
The takeaway: both drug classes affect bone quality and healing. What this means is that the type of medication, the dose, and the duration all shape the plan, not the name of the drug alone.
What Does an Implant Consultation Actually Look Like When Medications Are Involved?
When a patient takes a blood thinner, anticoagulant, or bone medication, the consultation changes in specific, predictable ways. Knowing those steps before the appointment makes the conversation easier.
The medication review is not a formality. Each drug class triggers a different planning step: anticoagulants prompt coordination with the prescribing physician about bridging or dose timing; bone medications prompt a MRONJ risk screen; GLP-1 drugs prompt an anesthesia protocol review for delayed gastric emptying. Disclosure happens early. The plan adjusts before surgery is scheduled, not after a complication surfaces.
Why Do Dentists Give Such Different Answers About the Same Bone Medication?
Oral bisphosphonate therapy alone is not a contraindication for dental implants per published professional guidelines, yet many patients are still told the opposite at their first appointment.
The gap between what the guidelines say and what some patients hear is one of the most frustrating patterns we encounter in this specialty area. A patient walks into an orthodontist's office having taken Fosamax (alendronate) for just eight weeks and is told, without any individualized assessment, that she is not a candidate for any dental treatment. No discussion of duration. No referral to an oral surgeon. No exploration of alternatives. Just a blanket denial, with one provider citing the number of lawsuits as the reason.
This happens more than it should. Well, that is not how evidence-based care is supposed to work!
According to the patient discussion in the r/osteoporosis community, a Canadian woman recently encountered exactly this scenario. The ADA guidelines cited in that thread state clearly: "Oral bisphosphonate therapy is not a contraindication for dental implants or oral surgery." The same guidelines note that the risk of osteonecrosis may increase with long-term use (defined as more than three years) or in combination with other risk factors like steroid use. Eight weeks of Fosamax does not meet that threshold.
The lifetime-ban scenario is even more extreme when it involves intravenous bisphosphonates used in cancer care. A 39-year-old breast cancer patient, after completing treatment with Zometa, was told by a dental oncology clinic dentist that she could "never" have dental surgery again. Her own oncologist disagreed. Virtually every commenter in her support community who had clinical knowledge contradicted the blanket ban, describing it instead as a timing issue around infusions.
The takeaway here is important. ONJ is real, and the risk deserves serious discussion. What this means in practice, though, is that providers owe patients an individualized assessment based on duration, drug type (oral vs. IV), and whether other risk factors are present, not a lawsuit-avoidance reflex.
If you have received a blanket denial based solely on bisphosphonate use, a second opinion from a provider who is willing to read your full chart rather than your prescription label is entirely appropriate. The question is never just "are you on this drug?" It is "what has your exposure actually been?"
MEDICATION READINESS QUICK-CHECK

Before your implant consultation:
1. List every medication: name, dose, and duration
2. Flag any bisphosphonates and note how long you have been taking them
3. Include all supplements
4. Note your most recent HbA1c if you manage diabetes
5. Contact your prescribing physician for GLP-1 drugs or blood thinners
How Do SSRIs, Blood Thinners, and Weight-Loss Drugs Each Change the Implant Plan?
SSRIs, blood thinners, and GLP-1 weight-loss medications each reshape the implant plan in completely different ways, and none of them automatically disqualify a patient from treatment.
Most patients are surprised to learn that antidepressants show up in the implant-failure research at all. A cohort study highlighted in pharmacology training for implant clinicians found that patients who used SSRIs daily had an implant failure rate of 10.6%, compared to 4.6% for non-users. That is roughly double the failure rate, and it persisted after the researchers adjusted for smoking, age, and gender (p = 0.03). Eight out of ten of those failures occurred between the fourth and fourteenth month after placement, not immediately, which means the implant looked healthy at first and then lost integration once it was put under load.
The mechanism, also detailed in pharmacology-focused clinical education, involves serotonin receptors on bone cells themselves. SSRIs block serotonin transporters, which in turn stimulates bone-breakdown cells (osteoclasts) while inhibiting bone-building cells (osteoblasts). Over time, SSRIs are associated with an annual reduction in bone mass of 0.62% to 0.93%. In practice, this means that a patient who has been on Paxil or Prozac for several years may have less bone-building capacity than their imaging suggests.
The takeaway: SSRI use is a risk flag, not a disqualifier. What this means for our patients is an extended monitoring schedule post-placement and a more thorough bone augmentation assessment upfront.
Blood thinners work differently. The concern there is not about bone biology at all. Anticoagulants (warfarin and newer agents) raise the risk of surgical bleeding, and the standard protocol is to coordinate with the prescribing physician about a temporary pause before the procedure. Pre-surgical timing of approximately 48 hours is commonly referenced, though the exact protocol depends on the specific medication and the patient's thromboembolic risk. The implant plan changes to accommodate that window. Candidacy does not change.
GLP-1 medications like Wegovy (semaglutide) raise a third, completely different concern: anesthesia safety. As a dental hygienist PSA widely shared in weight-loss communities noted, GLP-1 drugs cause delayed gastric emptying, which means food moves through the stomach more slowly and the risk of aspiration during sedation rises. Patients on these medications must disclose them to their surgical team well before any implant procedure that involves sedation. The implant is fine. The anesthesia plan is what needs to change.
What Changes When You Disclose a Blood Thinner Before Implant Surgery?
Disclosing a blood thinner before implant surgery shifts the protocol, not the outcome. The implant still happens, just with physician-coordinated preparation in place first.
Before disclosure: The patient arrives without flagging their anticoagulant. No pre-surgical coordination happens. The surgeon proceeds without knowing a pause is needed. Bleeding risk during and after placement rises significantly. The procedure may be interrupted or rescheduled.
After full disclosure: The prescribing physician is contacted in advance. A pause of roughly 48 hours is coordinated for common anticoagulants. The implant is placed on schedule. The healing environment is appropriate and the risk is managed before the first incision.
The medication review does not delay implant care. It is what makes implant care safe.
What Should a Thorough Medication Review Include Before You Sign Off on an Implant Plan?
A complete medication review covers every prescription, over-the-counter drug, and supplement, because what seems unrelated to your teeth often is not.
Did you know that a clinician who plans implant surgery without knowing your full medication list is already working at a disadvantage? The surgeon must know what precautions to take well before the procedure, not the morning of. The medication review is not a formality. It is where the real plan gets built.
Here is what a complete pre-implant medication disclosure should include:
| Category | Why It Matters | What to Bring |
|---|---|---|
| Bone medications | Bisphosphonates and RANK-L inhibitors affect bone remodeling and MRONJ risk | Drug name, dose, duration, oral vs. IV |
| Blood thinners | Raise surgical bleeding risk; require physician-coordinated pause | Drug name, dose, prescribing physician contact |
| Antidepressants (SSRIs) | Affect bone remodeling; linked to higher post-placement failure rates | Drug name, duration of use |
| Corticosteroids | Reduce bone density; combine with bisphosphonates to raise MRONJ risk | Drug name, whether use is short- or long-term |
| GLP-1 / weight-loss drugs | Delayed gastric emptying = anesthesia aspiration risk | Drug name, dosing schedule |
| Immunosuppressants | Impair wound healing and osseointegration | Drug name, condition being treated |
| Diabetes medications | Controlled vs. uncontrolled status changes healing outcomes | Most recent HbA1c result |
| Supplements | Some affect clotting (fish oil, vitamin E, ginkgo) | Full supplement list including doses |
As a clinical framework for candidacy assessment, it is worth stating plainly: controlled systemic conditions like diabetes and hypertension are not contraindications for implant surgery. Management status matters more than the diagnosis itself. An HbA1c within an acceptable range changes the picture entirely.
In practice, this also means that patients considering implant procedures at low-cost overseas destinations should know what the pre-surgical review at home would include. The success rates cited for dental tourism implants (around 95% to 98%) are based on populations with thorough pre-op screening. Skipping that step in pursuit of a lower price point is not the same bargain it appears to be.
The takeaway: bring everything to the consultation, including supplements. What this means is that a good implant plan starts not in the operatory but with the intake form.
| Risk Tier | Drug Class | Common Examples | Planning Impact | Action Required |
|---|---|---|---|---|
| Tier 1 | Blood thinners, controlled diabetes, controlled hypertension | Warfarin, Eliquis, Xarelto; metformin | Surgical bleeding risk; blood glucose and blood pressure management | Protocol adjustment; physician coordination |
| Tier 2 | Oral bisphosphonates (<3 years), SSRIs, short-term corticosteroids | Fosamax, Boniva, Actonel; fluoxetine, sertraline; prednisone (short-term) | Bone remodeling affected; elevated implant failure risk | Enhanced screening; extended post-placement monitoring |
| Tier 3 | IV bisphosphonates, RANK-L inhibitors, long-term steroids, immunosuppressants | Zometa, Reclast, Aredia; Prolia; prednisone (long-term) | Elevated MRONJ risk; bone quality may be worse than imaging reveals | Specialist consultation required before surgical planning |
| Tier 4 | GLP-1 receptor agonists (weight-loss and type 2 diabetes drugs) | Ozempic, Wegovy, Mounjaro (semaglutide, tirzepatide) | Delayed gastric emptying creates anesthesia aspiration risk | Dedicated anesthesia protocol adjustment required |
What Will Change for Dental Implant Candidates in the Next 12 to 24 Months?
Implant candidacy screening is shifting from a provider-by-provider judgment call toward standardized medication protocols, with SSRI use and bisphosphonate-steroid combinations at the center of that change.
Three signals are worth watching now:
- SSRI use will become a documented pre-surgical risk factor. Most implant intake processes today treat antidepressant use as general health background rather than a distinct surgical variable. According to pharmacology research highlighted in implant clinician training, daily SSRI users show implant failure rates roughly double those of non-users, tied to serotonin's effect on bone cell activity at the osteoblast and osteoclast level. That finding is significant enough that practices without explicit SSRI screening in their intake process are likely to add it. For patients: expect your antidepressant history to shape both pre-surgical imaging and the post-placement monitoring interval.
- Patients on bisphosphonates will face inconsistent access longer than guidelines suggest. Published guidance already states that oral bisphosphonate therapy alone is not a contraindication for implant surgery. Patient accounts continue to surface outright denials and permanent bans, including from oncology teams managing bone therapies, even when the clinical basis for that denial is not supported by the guidelines. That gap between written guidance and frontline practice is not closing quickly. A second opinion or specialist referral remains a reasonable and frequently warranted step.
- Combination drug regimens will draw more clinical scrutiny. Bisphosphonate therapy combined with long-term corticosteroid use is emerging as a distinct higher-risk group. Long-term steroids reduce bone density beyond what standard imaging reveals, and when combined with antiresorptive medications, the MRONJ risk profile is materially elevated compared to either drug alone. Practices are beginning to treat this combination as a specialist referral trigger rather than a standard enhanced-screening case.
What most patients overlook: providers who are most rigorous about medication disclosure requirements also tend to have the most predictable long-term outcomes. Conservative intake screening is not an obstacle to implant care. It is the mechanism that keeps failure rates low.
The 12-24 months Outlook, As We See It
Where dental implant medication rules are heading
Three forecasts on how medications and health conditions, not age, will keep reshaping dental implant treatment plans over the next two years.
Medication-driven implant forecasts
Use these forecasts to gauge how your medication history could change your implant timeline, risk, or eligibility before you commit to treatment.
Despite ADA guidance that oral bisphosphonate therapy alone is not a contraindication for implants, dental and oncology providers will continue denying or permanently barring implant surgery for patients with any bisphosphonate history, more conservatively than the guidance itself.
Over the next two years, patients on both antiresorptive drugs and long-term steroids will increasingly be treated as a distinct higher-risk group for implant planning, beyond what imaging alone would suggest.
Within 12-24 months, more dental implant intake processes will treat daily SSRI use as a distinct risk factor, citing failure rates roughly double those of non-users, rather than folding it into general health history.
Small Clues Worth Watching A cited cohort study found a 4.6% implant failure rate for non-SSRI users versus 10.6% for daily SSRI users (p=0.04), tied to SSRIs' effect on osteoblast and osteoclast activity. Patients on Fosamax and Zometa report outright denial or being told they can 'never' have dental surgery again, even though cited ADA guidance only flags elevated risk after 3+ years of use or with combined risk factors like steroids. Guidance notes osteonecrosis risk rises with long-term bisphosphonate use or when combined with steroid use, while separate reporting notes long-term steroids reduce bone density in ways standard scans may not fully capture.
Supporting and counter evidence
Each forecast below is paired with patient reports, clinical guidance, and research that support or challenge it.
- Fosamax and dentists is the strongest public backing for this call. [Community / Forum]Original poster (u/Emergency-Rip-6454, Canadian) was diagnosed with osteoporosis 6 months prior and prescribed Fosamax, starting in February - had taken only 8 weekly tablets (~8 weeks) when treatment was denied. “I would not be able to afford the lawsuit if you died, and my office isn't equipped to do the work there.”
- The case rests on I have a dental issue. [Community / Forum]
- Zometa and lifetime dental surgery ban? points the same way. [Community / Forum]OP (username rememberyes) is 39, diagnosed stage 2B breast cancer, now considered cured; was undergoing dental clearance for Zometa (zoledronic acid, a bisphosphonate) at a cancer hospital dental clinic. “the dentist absolutely blindsided me by telling me that once I've had bisphosphonate treatments, I will never be able to have dental surgery again.”
- Backing it: Guidelines for Medication-Related Osteonecrosis Jaw: An Update. [Industry Publication]"The medical use of bisphosphate drugs, both I.V. and oral, along with other antiresorptive and antiangiogenic drugs for the treatment of cancer and osteoporosis, has increased rapidly over the past 20-plus years.".
- Could Your Medication Be Causing Implant Failure? #Shorts is the strongest public backing for this call. [Video]Certain medications alter how bone heals, grows, and responds to dental implant surgery (speaker's central claim). “Most people have no idea their medications directly affect their jaw bone and nobody is warning them.”
- 12 Pharmacology Facts that Impact Dental Implant Therapy points the same way. [Video]SSRIs (both older ones like Paxil and Prozac and newer variants) affect bone because serotonin receptors exist on osteoblasts in bone, not just in the central nervous system. “if a patient is on a selective serotonin reuptake inhibitor it's going to affect the bone”
- The case rests on Could Your Medication Be Causing Implant Failure? #Shorts. [Video]Bisphosphonates, prescribed for osteoporosis, slow bone cell activity; this suppression can cause the bone integration/growth around an implant to fail.
What could shift these forecasts
These predictions could shift if clinical guidelines, drug prescribing patterns, or provider risk tolerance change.
Keeping It Real
71 has the most evidence behind it, but keep an eye on 71, since that is where we are least certain.
- A reversal by regulators or buyers undercuts Providers keep denying care beyond what guidelines require before anything else.
- If the balance of sources tips against the consensus, Providers keep denying care beyond what guidelines require becomes the safer call.
Frequently Asked Questions
Can I get dental implants if I take Prolia for osteoporosis?
Prolia (denosumab) is a RANK-L inhibitor, placing it in the same category of clinical concern as IV bisphosphonates. Specialist consultation before implant planning is standard when this drug is involved. Duration and any concurrent corticosteroid use are the key risk factors your team will assess.
What is MRONJ, and does it affect dental implant planning?
MRONJ (medication-related osteonecrosis of the jaw) is a rare condition where jaw bone fails to heal after surgery. Antiresorptive medications and certain antiangiogenic cancer drugs are associated with elevated risk. Risk rises with longer drug duration and when combined with steroids.
Does taking Ozempic or Wegovy change anything about implant surgery?
GLP-1 drugs delay gastric emptying, which creates anesthesia aspiration risk during any surgical procedure. Disclosing GLP-1 medication at the consultation allows the surgical team to adjust the protocol. This is not a disqualification from implant treatment.
Do all implant providers screen medications before surgery?
Published implant success rates are based on populations that received thorough pre-surgical screening. Skipping that step is not the same clinical procedure, even when the implant hardware is identical. Screening thoroughness is part of the outcome equation.
Key Takeaways
Key Takeaways
- Age alone is not an implant contraindication. Medications and systemic health predict outcomes more reliably.
- Oral bisphosphonate therapy alone is not a bar to implant placement per published professional guidelines.
- Blood thinners require a physician-coordinated pre-surgical pause, not a cancellation of the implant plan.
- A complete disclosure includes every prescription, supplement, and over-the-counter drug, not just the obvious ones.
- GLP-1 drugs like Ozempic affect anesthesia safety and must be disclosed before surgery.
The argument this article started with holds: a complete medication list changes the implant plan more reliably than a patient's age. Bisphosphonates, SSRIs, long-term steroids, and GLP-1 medications do not share a single risk pathway. Each one alters different biology. That is why a yes/no screening question cannot replace a real medication review.
What the evidence builds toward, and what we see reflected in our Lawrenceville practice, is that the planning conversation is where outcomes are shaped. A late implant failure rarely surprises the biology. It surprises the plan that did not account for that biology in the first place. The patients who do best are the ones who showed up to the first consultation ready to have that conversation.
Bring your full medication list. We will take it from there.
Sources & Further Reading
Further Reading on Medications and Dental Implant Planning
These organizations publish updated clinical guidance on medication-related implant risk.
- AAOMS (American Association of Oral and Maxillofacial Surgeons) - position papers on bisphosphonate-related osteonecrosis of the jaw (MRONJ)
- American Dental Association (ADA) - clinical guidance on anticoagulants and pre-surgical medication management
- U.S. Food and Drug Administration (FDA) - drug safety communications on bisphosphonates and osteonecrosis risk
- NIH MedlinePlus - patient-friendly guides on dental surgery and medication interactions
Related Articles
Written by
Maria Rhode
Owner & President, Imagine Advanced Dental Arts
Passionate about delivering the best possible care to my patients. From my days in residency to owning a beautiful hi-tech dental office, I never stop learning and advancing myself and now my practice.
Connect on LinkedInSummarize This Article With AI
Open this article in your preferred AI engine for an instant summary.